
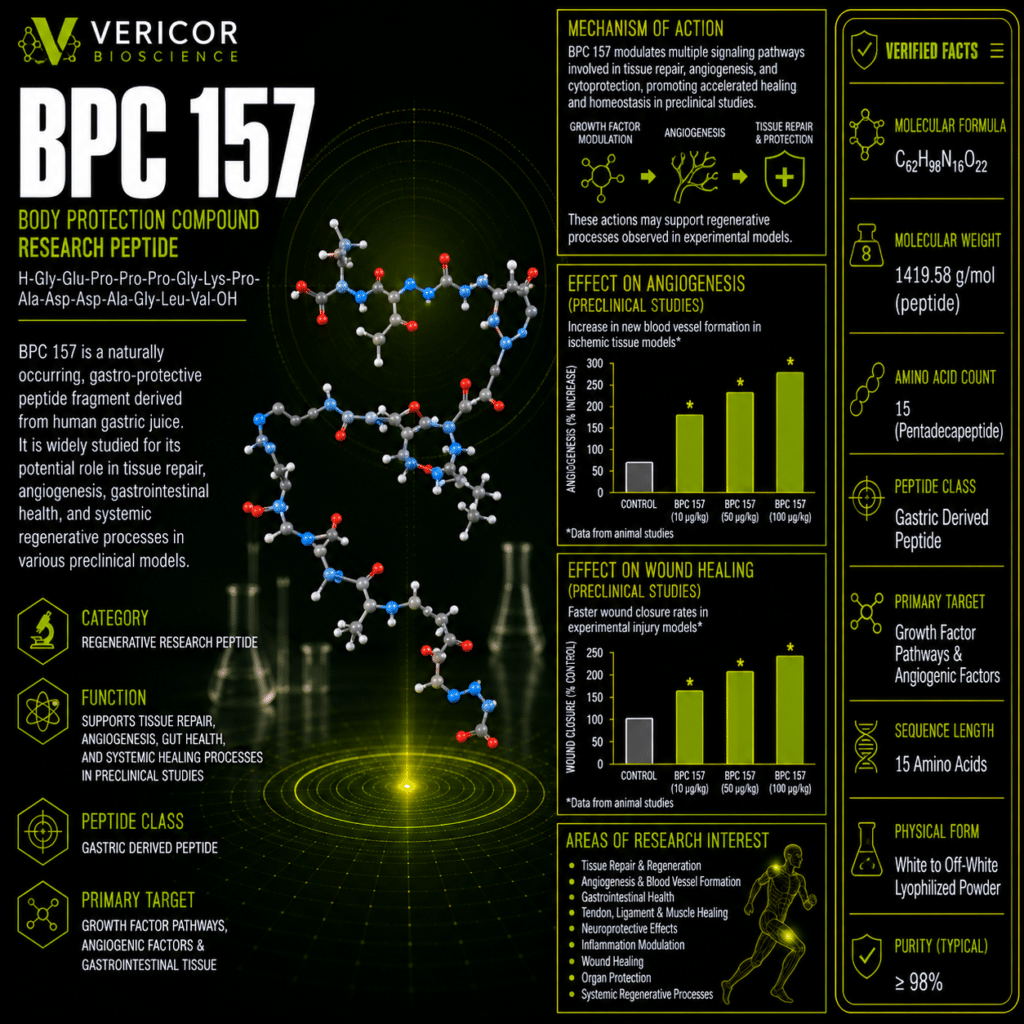
BPC-157 is an experimental peptide widely promoted in the United States for tendon repair, muscle recovery, joint pain, wound healing, and digestive health. However, most supporting evidence comes from laboratory and animal studies. BPC-157 is not an FDA-approved medication, and researchers have not established a safe, effective human dose for any medical condition.
Online discussions often describe this peptide as a powerful healing compound. Yet the quality of evidence matters more than the number of claims. Animal experiments can identify potential mechanisms, but they cannot confirm that a substance safely repairs injuries or treats gastrointestinal disease in people.
From reviewing the published evidence, the largest gap is clear: BPC-157 has generated substantial preclinical interest, but controlled human research remains extremely limited. Therefore, consumers, athletes, researchers, and healthcare professionals should distinguish promising hypotheses from proven clinical outcomes.
Featured Definition: What Is BPC-157?
BPC-157 is a synthetic 15-amino-acid peptide studied mainly in laboratory and animal models. Researchers have investigated its possible effects on blood vessels, inflammation, tendons, muscles, nerves, and digestive tissues. However, BPC-157 is not FDA approved, and reliable evidence about human effectiveness, dosing, and long-term safety remains limited.
Table of Contents
- What BPC-157 is
- Where BPC-157 comes from
- How BPC-157 may work
- BPC-157 and blood-vessel signaling
- Tendon and ligament research
- Muscle-recovery research
- Joint-pain evidence
- Wound-healing research
- Digestive and ulcerative-colitis claims
- Nerve and brain research
- Human evidence for BPC-157
- FDA and U.S. regulatory status
- BPC-157 and sports rules
- Product forms compared
- Safety concerns and unknown risks
- How to evaluate BPC-157 claims
- People Also Ask
- Expert Q&A
- Conclusion
What Is BPC-157?
BPC-157 is a synthetic peptide composed of 15 amino acids. For this reason, it is also called a pentadecapeptide.
Its commonly reported amino-acid sequence is:
Gly-Glu-Pro-Pro-Pro-Gly-Lys-Pro-Ala-Asp-Asp-Ala-Gly-Leu-Val
Peptides are short chains of amino acids. Proteins also consist of amino acids, but they are usually larger and have more complex structures.
The term “BPC” is commonly expanded as “body protection compound.” Researchers have described the sequence as being related to compounds studied in gastric juice. However, commercially synthesized BPC-157 should not be presented as though it were an established natural human hormone or approved replacement therapy.
The peptide does not have an identified nutritional requirement. In addition, there is no recognized medical diagnosis of “BPC-157 deficiency.”
Where Does BPC-157 Come From?
BPC-157 is generally produced through chemical peptide synthesis.
During peptide synthesis, amino acids are linked in a specific order. The resulting material must then be purified, characterized, and tested.
Even though BPC-157 contains only 15 amino acids, producing a reliable research material requires control over several factors:
- Amino-acid sequence
- Chemical identity
- Peptide purity
- Related peptide impurities
- Residual solvents
- Water content
- Salt or counterion form
- Aggregation
- Degradation
- Storage stability
- Microbial contamination
- Endotoxins
A printed purity percentage does not answer all these questions.
For example, a product may test as chemically pure but still contain bacterial endotoxins. It may also be incorrectly concentrated, degraded, contaminated during filling, or unsuitable for sterile administration.
This distinction becomes especially important when online sellers promote research materials for injection.
Why Is BPC-157 So Popular?
BPC-157 became popular through online fitness communities, sports-recovery forums, social media, anti-aging clinics, and peptide vendors.
Common claims include faster recovery from:
- Tendon injuries
- Ligament injuries
- Muscle strains
- Joint pain
- Surgical procedures
- Stomach ulcers
- Inflammatory bowel disease
- Nerve injuries
- Skin wounds
- Bone injuries
These claims often refer to animal studies. However, marketing pages may remove the words “rat,” “mouse,” or “experimental model,” making the findings sound like established human treatment results.
BPC-157 also appeals to consumers because it is often described as a substance that coordinates the body’s natural healing systems. That description is attractive but too broad to be treated as a medical fact.
Healing involves inflammation, blood flow, collagen production, immune activity, cell migration, tissue remodeling, and mechanical loading. A substance that changes one pathway may not improve the entire healing process.
How Might BPC-157 Work?
Researchers have proposed that BPC-157 may affect several signaling systems.
Potential mechanisms discussed in preclinical research include:
- Nitric-oxide signaling
- Blood-vessel formation
- Growth-factor activity
- Inflammatory signaling
- Cell migration
- Collagen organization
- Oxidative stress
- Neurotransmitter systems
- Gastrointestinal protection
However, the complete molecular mechanism has not been established.
A medicine normally has a defined pharmacological profile that explains:
- How it enters the body
- How it reaches the target tissue
- Which receptor or enzyme it affects
- How strongly it affects that target
- How the body metabolizes it
- How quickly it is eliminated
- Which dose creates a clinical effect
- Which dose creates unacceptable toxicity
For BPC-157, major gaps remain in absorption, distribution, metabolism, excretion, receptor binding, and dose-response data in humans. A recent scientific review described substantial translational and drug-development barriers despite the peptide’s extensive preclinical literature.
BPC-157 and Nitric-Oxide Signaling
Nitric oxide is a signaling molecule involved in blood-vessel relaxation, blood flow, platelet activity, nerve communication, and immune responses.
Some animal experiments suggest BPC-157 may interact with the nitric-oxide system. Researchers have proposed that this interaction may help explain observations involving circulation, gastrointestinal protection, and tissue injury.
However, nitric-oxide signaling is not simply beneficial or harmful.
Too little nitric oxide can impair circulation. Meanwhile, excessive or poorly regulated nitric-oxide activity can contribute to inflammation, oxidative stress, low blood pressure, and tissue damage.
Therefore, a claim that BPC-157 “boosts nitric oxide” does not establish a safe healing benefit. Researchers must determine where the effect occurs, how strong it is, how long it lasts, and whether it improves clinical outcomes.
BPC-157 and Blood-Vessel Formation
Tissue repair often requires angiogenesis, which is the formation of new blood vessels from existing vessels.
New blood vessels can deliver oxygen, nutrients, immune cells, and growth signals to damaged tissue. Consequently, angiogenesis can support wound repair under appropriate conditions.
Preclinical studies have reported vascular responses associated with BPC-157. Researchers have discussed possible interactions with vascular endothelial growth factor, commonly called VEGF, and related signaling pathways.
Nevertheless, angiogenesis is biologically complex.
New blood-vessel formation may support healing, but uncontrolled vascular growth is associated with conditions such as cancer, diabetic eye disease, and other disorders. This does not prove BPC-157 causes those conditions. Instead, it shows why long-term safety research is necessary before describing angiogenic effects as universally beneficial.
BPC-157 Tendon Research
Tendon recovery is one of the most common reasons people search for BPC-157.
Tendons are strong bands of connective tissue that attach muscles to bones. They contain densely organized collagen fibers designed to transfer mechanical force.
Tendon healing can be slow because tendons generally have a more limited blood supply than many other tissues. Recovery may also be affected by age, diabetes, smoking, medications, injury severity, activity, and rehabilitation quality.
Animal studies have examined BPC-157 after tendon injury or surgical tendon damage. Some experiments reported improvements in structural, mechanical, or functional measurements.
However, these findings do not prove that BPC-157 heals human tendon injuries.
Animal tendons differ from human tendons in size, loading patterns, biology, and recovery time. In addition, researchers may create highly standardized injuries that do not match chronic tendinopathy in people.
Chronic tendinopathy is not simply a fresh tear. It may involve altered collagen, failed tissue remodeling, pain sensitization, reduced mechanical capacity, and repeated overload.
A high-quality human trial would need to measure:
- Pain
- Strength
- Functional performance
- Return-to-activity time
- Imaging changes
- Reinjury
- Adverse effects
- Long-term tendon quality
Current research has not established BPC-157 as an accepted treatment for Achilles, patellar, rotator-cuff, elbow, or other tendon conditions. A recent narrative review concluded that well-designed human trials are still needed before the peptide can have a defined role in musculoskeletal medicine.
Can BPC-157 Repair Ligaments?
Ligaments connect bones to other bones and help stabilize joints.
As with tendons, laboratory and animal findings have encouraged claims that BPC-157 may improve ligament recovery. Yet the evidence is not sufficient to recommend it for anterior cruciate ligament injuries, ankle sprains, or other ligament problems.
Ligament recovery depends on:
- Tear severity
- Joint stability
- Blood supply
- Alignment
- Rehabilitation
- Muscle strength
- Activity demands
- Surgical decisions
A peptide cannot be assumed to restore mechanical stability after a complete ligament rupture.
In some cases, reducing pain without restoring strength could even create risk if a person returns to activity too early.
Therefore, pain relief, tissue appearance, and true functional repair should be evaluated separately.
BPC-157 and Muscle Recovery
Animal studies have investigated BPC-157 in models of muscle injury.
Researchers have reported findings involving muscle healing, functional recovery, blood supply, and tissue organization. However, these are preclinical observations rather than proof of faster recovery in athletes or patients.
Muscle soreness after exercise is also different from a traumatic muscle tear.
Delayed-onset muscle soreness usually develops after unfamiliar or intense activity. It often resolves with time, sleep, nutrition, and appropriate training adjustments.
In contrast, a muscle strain may involve actual fiber disruption and require graded rehabilitation.
Current evidence does not establish that BPC-157:
- Increases muscle growth
- Improves strength
- Prevents soreness
- Shortens recovery after every workout
- Repairs major muscle tears
- Improves athletic performance
Claims in these areas should be labeled experimental.
BPC-157 and Joint Pain
A small retrospective chart review examined intra-articular BPC-157 injections in patients with knee pain. Some patients reportedly described improvement. However, the study lacked randomization, a placebo group, standardized follow-up, and strong controls for bias. Some participants also received another peptide, making the specific effect of BPC-157 difficult to determine.
Retrospective reports can generate research questions, but they cannot establish effectiveness.
Knee pain can arise from:
- Osteoarthritis
- Tendon disease
- Meniscus injury
- Ligament injury
- Referred pain
- Inflammatory arthritis
- Infection
- Gout
- Bone injury
Without a clear diagnosis, a reported improvement does not show which condition responded or why.
In addition, joint injections have procedural risks, including infection, bleeding, tissue damage, and temporary inflammation.
BPC-157 is not an FDA-approved intra-articular therapy.
BPC-157 and Wound Healing
Wound healing occurs in overlapping phases:
- Hemostasis
- Inflammation
- New-tissue formation
- Remodeling
Hemostasis stops bleeding. Inflammation removes damaged material and helps prevent infection. New tissue and blood vessels then develop. Finally, collagen is reorganized during remodeling.
Animal research has explored BPC-157 in skin wounds, surgical connections, burns, and other injury models. Positive preclinical reports have involved blood-vessel responses, collagen, and wound closure.
However, wound outcomes depend on much more than peptide signaling.
Important factors include:
- Blood circulation
- Infection
- Diabetes
- Nutrition
- Smoking
- Pressure
- Wound depth
- Tissue death
- Medication use
- Foreign material
A product that appears helpful in an animal incision cannot automatically treat a diabetic foot ulcer, pressure wound, surgical infection, or severe burn.
Delayed medical treatment for a wound can lead to infection, tissue loss, hospitalization, or amputation. Therefore, experimental peptides should not replace professional wound assessment.
BPC-157 and Bone Healing
Some preclinical studies have investigated bone defects, fractures, or bone-tendon healing.
Bone repair requires inflammation, blood-vessel formation, mineralization, mechanical stability, and remodeling. Animal findings may suggest a possible research direction, but they do not prove that BPC-157 speeds human fracture healing.
Fracture care depends on:
- Bone alignment
- Stability
- Blood flow
- Infection status
- Calcium and vitamin D status
- Hormonal health
- Smoking
- Age
- Weight-bearing instructions
An unstable or displaced fracture may require reduction or surgery. Delaying appropriate orthopedic care can cause deformity, nonunion, nerve damage, or chronic disability.
BPC-157 and Digestive Health
BPC-157 research began largely within gastrointestinal models. Consequently, the peptide is promoted online for ulcers, gastritis, inflammatory bowel disease, “leaky gut,” and intestinal healing.
Animal studies have examined:
- Stomach injury
- Intestinal inflammation
- Surgical intestinal connections
- Medication-related gastrointestinal damage
- Fistulas
- Ulcers
Some experiments reported protective or healing-related findings.
Nevertheless, digestive conditions have very different causes.
For example:
- Peptic ulcers may involve Helicobacter pylori or anti-inflammatory drugs.
- Crohn’s disease is a chronic immune-mediated condition.
- Ulcerative colitis affects the colon and rectum.
- Celiac disease is triggered by gluten in genetically susceptible people.
- Irritable bowel syndrome does not cause the same tissue inflammation as inflammatory bowel disease.
A single peptide cannot be assumed to treat all these disorders.
BPC-157 and Ulcerative Colitis
Ulcerative colitis is a chronic inflammatory disease of the colon.
Symptoms may include:
- Bloody diarrhea
- Urgency
- Abdominal pain
- Fatigue
- Weight loss
- Anemia
The condition can range from mild to severe. Complications may include hospitalization, severe bleeding, toxic megacolon, blood clots, and increased colorectal-cancer risk over time.
In July 2026, FDA materials evaluated BPC-157 free base and BPC-157 acetate in relation to proposed compounding for ulcerative colitis. The agency’s evaluation stated that available criteria weighed against adding either substance to the federal 503A Bulks List. The FDA cited limited evidence of effectiveness and unresolved safety and quality concerns, including uncertainties involving impurities and peptide aggregation.
The committee process does not represent approval of BPC-157 for ulcerative colitis. Readers can examine the FDA BPC-157 compounding evaluation for the agency’s current analysis.
Patients should not replace prescribed ulcerative-colitis treatment with BPC-157. Stopping effective medication can lead to a serious disease flare.
BPC-157 and the Brain-Gut Axis
The brain and digestive system communicate through nerves, hormones, immune signals, and microbial metabolites. This network is often called the brain-gut axis.
Animal research has discussed BPC-157 in connection with neurotransmitter pathways, behavior, nerve injury, and gastrointestinal signaling.
Researchers have proposed interactions involving:
- Dopamine
- Serotonin
- Nitric oxide
- GABA-related signaling
- Stress responses
However, these proposed mechanisms do not establish BPC-157 as a treatment for depression, anxiety, addiction, traumatic brain injury, Parkinson’s disease, or another neurological condition.
Brain-related symptoms require careful evaluation. For example, anxiety, sleep changes, cognitive problems, or mood symptoms may be related to medical conditions, medications, substance use, or psychiatric disorders.
Experimental peptide use may delay diagnosis or interact unpredictably with treatment.
BPC-157 and Nerve Healing
Animal studies have examined peripheral-nerve injuries and functional recovery after nerve damage.
These findings are preliminary.
Human nerve injuries vary widely. A compressed nerve, severed nerve, diabetic neuropathy, spinal-cord injury, and medication-related neuropathy are not equivalent.
A valid human trial would need objective measures such as:
- Nerve-conduction testing
- Muscle strength
- Sensory function
- Pain
- Functional recovery
- Imaging
- Long-term adverse events
Current evidence does not establish BPC-157 as a neurological treatment.
What Human BPC-157 Evidence Exists?
Human data are extremely limited compared with the large number of animal publications.
A 2025 pilot study administered intravenous BPC-157 to only two healthy adults. The participants reportedly experienced no measurable adverse effects in the assessed laboratory markers and reported no side effects. However, a two-person study cannot establish general safety, detect uncommon reactions, identify long-term risks, or prove effectiveness.
The study is useful as an early observation, but its limitations are substantial:
- Only two participants
- No treatment-effect evaluation
- No placebo comparison
- Very limited ability to detect adverse events
- Short observation period
- No evidence for injured or ill patients
- No evidence for repeated long-term use
Another human report involved a retrospective review of knee injections. It lacked the controls needed to determine whether the peptide caused the reported improvement.
Therefore, claims that “human studies prove BPC-157 is safe” overstate the evidence.
Laboratory, Animal, and Human Evidence Compared
| Evidence level | What it can show | What it cannot prove | Current BPC-157 evidence |
|---|---|---|---|
| Chemical analysis | Identity and purity | Human safety or benefit | Research materials can be characterized |
| Cell studies | Cellular mechanisms | Whole-body effectiveness | Limited compared with animal literature |
| Animal studies | Biological effects in living models | Reliable human outcomes | Numerous injury and gastrointestinal models |
| Case reports | Individual observations | Cause and effect | Very limited |
| Retrospective studies | Patterns in existing records | Reliable treatment efficacy | One weak knee-pain report |
| Small pilot study | Early tolerability signals | General or long-term safety | Two-person IV report |
| Randomized clinical trials | Comparative benefits and risks | Every rare long-term outcome | Adequate trials are lacking |
| FDA approval | Reviewed use, manufacturing, and labeling | Suitability for every person | No FDA-approved BPC-157 drug |
The evidence hierarchy prevents early observations from being mistaken for treatment recommendations.
Is BPC-157 FDA Approved?
No. BPC-157 is not an FDA-approved medication for tendon injury, joint pain, muscle recovery, wound healing, ulcerative colitis, stomach ulcers, neurological conditions, or another use.
FDA materials state that neither BPC-157 free base nor BPC-157 acetate is a component of an FDA-approved drug. The agency has also raised safety and quality concerns when reviewing the substances for compounding.
An FDA substance database entry does not mean a drug is approved. Substance databases may record chemical identity without authorizing clinical use.
Likewise, an advisory-committee discussion does not create an approved medication. The Pharmacy Compounding Advisory Committee advises the FDA on technical and medical matters. The FDA makes final regulatory decisions through separate processes.
BPC-157 and Pharmacy Compounding
Compounding involves preparing a medication for an identified patient under specific federal and state requirements.
Compounded drugs are not FDA approved. The FDA does not review them for safety, effectiveness, and manufacturing quality before marketing in the same way it reviews approved drugs.
In its July 2026 briefing, the FDA concluded that the evaluation criteria weighed against placing BPC-157 free base and BPC-157 acetate on the 503A Bulks List.
The agency discussed concerns involving:
- Limited evidence of human effectiveness
- Limited human safety information
- Potential peptide impurities
- Possible aggregation
- Immunogenicity uncertainty
- Inconsistent substance identification
- Lack of recognized USP or NF monographs
Administrative and compliance questions about compounding should be reviewed by licensed pharmacy professionals and qualified regulatory counsel. This information is educational, not legal advice.
Is BPC-157 a Dietary Supplement?
BPC-157 should not be assumed to be a lawful dietary-supplement ingredient simply because it appears in capsules or tablets.
The FDA has issued warning letters involving businesses marketing BPC-157 products with disease-treatment claims. Such claims can cause a product to be regulated as a drug under U.S. law.
Terms such as these do not establish lawful supplement status:
- Natural
- Research-backed
- Wellness peptide
- Bioactive supplement
- Recovery formula
- Doctor formulated
Consumers should evaluate the ingredient, intended use, labeling, claims, and regulatory category rather than relying on promotional language.
BPC-157 and Sports: Is It Prohibited?
Yes. BPC-157 is prohibited in sports governed by the World Anti-Doping Agency Code.
The United States Anti-Doping Agency identifies BPC-157 under the S0 category for non-approved substances. It is prohibited at all times, including both in and out of competition.
Athletes can review the USADA guidance on BPC-157 for current anti-doping information.
This concern applies not only to elite Olympic athletes. Anti-doping rules may affect collegiate competitors, professional athletes, tested amateur athletes, and participants under sport-specific policies.
A prescription from a clinic does not automatically make a prohibited substance acceptable under anti-doping rules.
Athletes remain responsible for substances found in their bodies. Therefore, they should consult their sport’s governing organization and use approved medication-checking resources before taking any peptide, supplement, or compounded product.
BPC-157 Product Categories Compared
| Product category | FDA approved? | Intended context | Key concern |
| FDA-approved BPC-157 drug | No | No approved medical indication | No approved label or standardized dose |
| Compounded BPC-157 | No | Subject to applicable compounding rules | FDA has recommended against 503A list inclusion |
| Research-grade BPC-157 | No | Laboratory and analytical research | Not intended for human use |
| “Research use only” vial | No | Nonclinical work | Should not be injected or consumed |
| Online capsule | No approved BPC-157 drug | Consumer marketing varies | Identity, claims, and quality may be uncertain |
| Unverified injectable vial | No | Often unclear | Sterility, endotoxins, potency, and contamination risks |
These categories are not interchangeable.
A research vial is not a prescription medicine. Likewise, a product sold by a wellness business is not automatically FDA approved.
BPC-157 Free Base vs. BPC-157 Acetate
BPC-157 may be described as free base or acetate.
The acetate form contains acetate as a counterion. This may affect:
- Molecular-weight calculations
- Solubility
- Stability
- pH
- Assay interpretation
- Formulation
- Labeled peptide content
The FDA considers BPC-157 free base and BPC-157 acetate different bulk drug substances. It also noted that submitted nominations had inconsistent information about which form was being proposed.
Researchers should verify the exact form rather than assuming every BPC-157 product is chemically equivalent.
Is BPC-157 Safe?
BPC-157’s safety has not been established through adequate human trials.
Online sources sometimes argue that it is safe because animal studies report few adverse effects. However, animal tolerability does not eliminate human risks.
Potential concerns include:
- Allergic reactions
- Immune responses
- Headache
- Nausea
- Dizziness
- Fatigue
- Injection-site reactions
- Blood-pressure changes
- Unexpected vascular effects
- Drug interactions
- Effects on abnormal tissue growth
- Contamination
- Incorrect concentration
The actual frequency of adverse events is unknown.
In addition, online users may combine BPC-157 with other experimental peptides. This makes it difficult to identify which substance caused a reaction.
Immunogenicity and Peptide Aggregation
Immunogenicity is the ability of a substance to trigger an immune response.
The body may form antibodies against an administered peptide. Those antibodies could reduce the peptide’s activity, cause allergic reactions, or potentially interact with similar natural molecules.
Peptide aggregation occurs when peptide molecules cluster together. Aggregates may change biological behavior and can increase immune-related concerns.
In its 2026 evaluation, the FDA stated that uncertainties about BPC-157 impurities and aggregation prevented the agency from ruling out immunogenicity risks.
These concerns cannot be addressed by a simple claim of “99% purity.”
A complete peptide-quality assessment may need to examine:
- Aggregate levels
- Truncated sequences
- Modified amino acids
- Oxidation
- Deamidation
- Residual chemicals
- Counterions
- Endotoxins
- Sterility
Risks of Injecting BPC-157
Injection creates risks beyond the peptide’s pharmacological activity.
Potential injection-related risks include:
- Skin infection
- Abscess
- Cellulitis
- Bloodstream infection
- Nerve injury
- Tissue damage
- Bleeding
- Endotoxin reactions
- Incorrect dosing
- Particulate contamination
A vial can look clear and still contain microorganisms, endotoxins, or invisible particles.
Furthermore, injecting near an injury does not guarantee that the peptide remains in that tissue or improves healing there.
Medical injections require an appropriate diagnosis, sterile technique, suitable formulation, trained administration, and a valid clinical reason.
Oral vs. Injectable BPC-157
| Feature | Oral BPC-157 | Injectable BPC-157 |
| Route | Swallowed | Injected under skin, into muscle, or sometimes into joints |
| Human absorption data | Inadequate | Inadequate |
| First-pass metabolism | Possible | Reduced for some injection routes |
| Sterility requirement | Not normally sterile | Sterility is essential |
| Procedure risks | Lower than injection | Infection, bleeding, and tissue injury |
| Established clinical dose | No | No |
| FDA-approved use | No | No |
| Proven effectiveness | No | No |
Some promoters claim BPC-157 is unusually stable in digestive conditions. Even so, stability does not prove that an oral product reaches target tissues at an effective concentration.
Likewise, injection bypasses digestion but does not solve questions about dose, distribution, metabolism, effectiveness, or safety.
Who Should Be Especially Cautious?
Because BPC-157 lacks adequate human safety data, self-experimentation is particularly concerning for:
- Pregnant people
- Breastfeeding individuals
- Children and adolescents
- People trying to conceive
- Patients with active cancer
- Cancer survivors
- People taking anticoagulants
- Organ-transplant recipients
- People using immunosuppressants
- Individuals with severe allergies
- Patients awaiting surgery
- People with liver or kidney disease
- Competitive athletes
This list is not complete.
The absence of a documented contraindication may simply mean the risk has never been adequately studied.
Can BPC-157 Interact With Medications?
Reliable human interaction studies are unavailable.
Theoretical concerns may involve medications affecting:
- Blood pressure
- Blood clotting
- Platelet function
- Inflammation
- Immune responses
- Blood-vessel growth
- Neurotransmitters
- Gastrointestinal healing
Extra caution may be appropriate with:
- Anticoagulants
- Antiplatelet drugs
- Anti-inflammatory medicines
- Blood-pressure medications
- Immunosuppressive treatments
- Cancer therapies
- Psychiatric medicines
- Other peptides
“No known interactions” is not equivalent to “proven to have no interactions.”
Patients should not stop prescription drugs to use BPC-157.
How to Evaluate a BPC-157 Claim
Use this numbered checklist before accepting a recovery or health claim.
- Identify the evidence type.
Determine whether the claim comes from cells, rodents, a case report, or a controlled human trial. - Confirm the exact injury or disease.
A rat tendon experiment does not prove benefit for human arthritis, ulcers, or nerve damage. - Check the product form.
Free base, acetate, capsules, and injections cannot be assumed equivalent. - Review the route.
Oral, subcutaneous, intravenous, and intra-articular administration produce different exposures and risks. - Look for a comparison group.
Without placebo or standard-care comparison, improvement may reflect natural healing or rehabilitation. - Examine meaningful outcomes.
A molecular marker is not the same as reduced pain, restored strength, or return to activity. - Check study independence.
Findings are more reliable when several unrelated research groups reproduce them. - Review human safety data.
A two-person pilot study cannot establish general safety. - Verify FDA status.
Compounding discussion, chemical registration, and online sale do not equal approval. - Consider sports rules.
Tested athletes should confirm anti-doping status before using any substance.
Common BPC-157 Marketing Red Flags
Be cautious when a website claims BPC-157:
- Heals every type of injury
- Repairs tendons in days
- Cures inflammatory bowel disease
- Has no side effects
- Is FDA approved
- Is legal because it is sold online
- Cannot be detected in sport
- Is safe because it is natural
- Works equally well orally and by injection
- Has a universally accepted dosage
- Prevents cancer
- Replaces surgery or rehabilitation
Other warning signs include:
- Instructions for injecting research material
- No identifiable manufacturer
- No lot number
- Unverifiable laboratory testing
- Certificates that test only purity
- Disease claims without human trials
- Testimonials presented as clinical evidence
More Reliable Injury-Recovery Strategies
For musculoskeletal injuries, an accurate diagnosis is often more valuable than an experimental product.
Depending on the condition, evidence-based management may include:
- Temporary activity modification
- Progressive rehabilitation
- Strength training
- Mobility work
- Adequate protein and calories
- Sleep
- Physical therapy
- Appropriate pain management
- Imaging when indicated
- Surgery for selected injuries
Recovery takes time because tissue must rebuild and adapt to mechanical load.
Pain reduction alone is not proof of complete healing. A tendon or ligament must regain the strength and capacity required for the person’s activities.
People Also Ask About BPC-157
BPC-157 is used primarily as an experimental research peptide. It is promoted for injury recovery and digestive health, but it does not have an FDA-approved medical use.
Animal studies have reported tendon-healing effects. However, adequate controlled human trials have not established that BPC-157 repairs tendon injuries safely or effectively in people.
BPC-157 is not an FDA-approved drug or established dietary-supplement ingredient. Its regulatory treatment depends on the product, intended use, claims, and distribution, while current FDA analysis weighs against its use under the 503A Bulks List.
Yes. BPC-157 is prohibited at all times under the WADA S0 category for non-approved substances. Tested athletes risk anti-doping consequences even when a clinic supplies the product.
Human evidence is extremely limited. Published reports include a two-person intravenous pilot study and a weak retrospective knee-injection report, neither of which establishes broad safety or clinical effectiveness.
Expert BPC-157 Q&A
1. Why do positive animal studies not prove BPC-157 works in humans?
Animals differ from humans in metabolism, immune function, injury size, activity, and tissue biology. Experimental injuries are also more standardized than real-world chronic conditions.
2. Can a certificate of analysis prove injectable BPC-157 is safe?
No. A certificate may report identity or chemical purity, but injectable safety also depends on sterility, endotoxins, aggregates, particles, potency, formulation, and container integrity.
3. Why is BPC-157’s effect on blood vessels important?
Blood-vessel signaling may contribute to tissue repair. However, vascular growth and nitric-oxide pathways also influence blood pressure, inflammation, eye disease, and tumor biology, so long-term effects require careful study.
4. Could BPC-157 reduce pain without healing an injury?
It is possible for pain and structural recovery to change at different rates. Therefore, symptom improvement alone cannot confirm that a tendon, ligament, muscle, or joint has regained normal strength.
5. What evidence would be required for FDA approval?
A developer would need standardized manufacturing, toxicology studies, pharmacokinetic data, dose-ranging trials, controlled clinical trials, adverse-event monitoring, and evidence that benefits outweigh risks for a defined indication.
BPC-157 and TB-500: Why Researchers Study Them Together
BPC-157 and TB-500 are frequently discussed together in the peptide research community, and for good reason. Both are stable synthetic peptides under active preclinical investigation for tissue repair, but they act through different biological pathways. BPC-157, derived from a partial sequence identified in human gastric juice, has been studied for its effects on angiogenesis and gastrointestinal protection in animal models. TB-500, related to a fragment of Thymosin Beta-4, has been researched for its role in actin regulation and cell migration during wound healing in preclinical studies.
Because their proposed mechanisms differ rather than overlap, some researchers investigate the two peptides within the same tissue-repair study designs, which is also why Vericor Bioscience offers a combined BPC-157 and TB-500 research blend alongside each compound individually. None of this research has been evaluated by the FDA, and none of it establishes safety or effectiveness in humans. For a closer look at TB-500’s own preclinical evidence and regulatory status, see our full TB-500 research guide.
BPC-157 and KPV in Gut-Inflammation Research
BPC-157 and KPV both appear in preclinical gastrointestinal-inflammation research, though they’ve been studied through different mechanisms. BPC-157 has been researched for cytoprotective and angiogenic effects in animal models of gastrointestinal injury, while KPV, a tripeptide fragment of alpha-melanocyte-stimulating hormone, has been studied for its potential to inhibit NF-κB signaling, a pathway implicated in inflammatory bowel conditions such as colitis.
Researchers investigating gut-inflammation models sometimes reference both compounds’ distinct preclinical literatures rather than choosing one over the other. As with all research covered here, this is animal-model and laboratory evidence only; it has not been reviewed by the FDA and does not establish safety or effectiveness in humans. See our full KPV research guide for more on its studied anti-inflammatory pathway.
Conclusion
BPC-157 is a synthetic 15-amino-acid peptide with an extensive body of animal research involving tendons, muscles, wounds, gastrointestinal tissues, blood vessels, and nerves.
The research is scientifically interesting. However, it does not establish BPC-157 as a proven human recovery treatment.
Human evidence remains exceptionally limited. A two-person pilot study cannot determine broad safety, while an uncontrolled knee-pain chart review cannot establish effectiveness. In addition, there is no accepted clinical dosage, no FDA-approved indication, and no robust long-term safety information.
The current U.S. regulatory context also deserves careful attention. In July 2026, the FDA concluded that available criteria weighed against adding BPC-157 free base and BPC-157 acetate to the 503A Bulks List. The agency identified unresolved concerns involving evidence, impurities, aggregation, and immunogenicity. Competitive athletes should also know that BPC-157 is prohibited under WADA’s non-approved-substances category.
Consumers should avoid interpreting online availability, clinic promotion, or research certificates as proof of medical approval. Likewise, research-grade materials should not be injected, swallowed, or used as substitutes for diagnosis, rehabilitation, or evidence-based treatment.
Researchers and qualified professional buyers can review the available specifications on the Vericor Bioscience BPC-157 research product page. Product information should remain within its stated research context and should not be interpreted as prescribing guidance or approval for human use.